
The Female Hormone Blueprint
16 weeks, five arms, one pick each
- Pathways5
- Weeks16
- Draw first15 markers
A theoretical research protocol. Not medical advice, and not for human use.
Which of these 5 is actually you?
This tells you where your biggest leverage is: where to start, not where to stop. Open a lane for the one thing it cannot do for you.
Luteal phase & progesterone support
The week before your period is the problem - mood, sleep, breast tenderness, spotting.
But Judged in cycles, not weeks. Three of them before you can say anything.
PCOS — insulin, androgens & ovulation
Irregular or absent cycles with acne, hair changes or weight that will not shift.
But PCOS is a diagnosis, not a self-assessment. The insulin half responds well; the androgenic half is slow.
Perimenopause & the estrogen decline
Over 40, cycles changing, night sweats, sleep falling apart, and nobody has offered you anything.
But None of this is HRT, and for many women HRT is the better answer. This lane is for supporting the transition, not replacing what is being lost.
Estrogen metabolism & clearance
Heavy periods, tenderness, fibroids - an estrogen-dominant pattern rather than a deficiency one.
But You are changing which metabolites are produced, not how much estrogen there is. That distinction matters.
Fertility & egg quality
You are trying to conceive, or planning to within the year.
But Egg quality responds over about 90 days - the follicle's own maturation window - so this is started early or not at all.
The stack
One pick per pathway, each linked. Run one arm or several; each folds out its options.
Most options here use this code. Each Shop link copies its own as the store opens.
The arms on this page are not additive — several are for different life stages and running two is incoherent.
Health supplements and substrate 5
Why this pick: the worked example
The best-evidenced supplement for PCOS there is. It acts as a second messenger in insulin signaling, and PCOS is at root an insulin problem expressing itself through androgens. Randomized trials show improved insulin sensitivity, lower androgens, and restored ovulation — the 40:1 myo-to-D-chiro ratio is what most of the trials used and it matters.
Start here if PCOS is the diagnosis
Daily, split dose, from week 1
The other lanes in this arm. Metformin has the longest history and comparable efficacy in trials — but it is prescription, the GI effects are worse, and inositol matches it in several head-to-head studies. Berberine works on the same insulin pathway. NAC improves insulin sensitivity and has ovulation-induction data. Alpha-lipoic acid is the other insulin-sensitizing option. Myo-inositol is the base because it matches the prescription option in trials while being over the counter and far better tolerated.
6 options: 0 to swap in, 6 to stack on
6 options: 0 to swap in, 6 to stack on
4 options: 0 to swap in, 4 to stack on
The bloodwork
3 draws, each its own cart; the later ones are folded below. The why for each draw is under “Why this blueprint” below.
Before you start
Everything, drawn before you start. This is the one that decides which pathway is actually yours - and the only one you cannot go back and collect later.
The 15 markers in it
LH & FSH, Estradiol, Standard (ECLIA), Progesterone, SHBG (Sex Hormone-Binding Globulin), Total Testosterone, Free Testosterone, DHEA-S, Anti-Müllerian Hormone (AMH), Prolactin, TSH (Thyroid-Stimulating Hormone), Thyroid Antibodies (TPO + TgAb), HbA1c (Hemoglobin A1c), Fasting Insulin, Ferritin, Vitamin D (25-Hydroxy).
15 markers, about $392 at list. Drawn at Quest, no doctor’s visit.
The free peptide field guide
The 12 compounds people ask about most: how each one works, what the research shows, the markers that say whether it is doing anything, and what most people get wrong.
After that it is about two emails a week: a marker, a compound or a protocol. Unsubscribe in one click.
Why it is built this way
Why this blueprint
Female hormonal complaints get lumped together and they are not one problem. PCOS is fundamentally an insulin and androgen problem that shows up as a cycle problem. Perimenopause is a declining and erratic estrogen problem. Luteal-phase symptoms are usually progesterone-relative-to-estrogen.
Female hormonal complaints get lumped together and they are not one problem. PCOS is fundamentally an insulin and androgen problem that shows up as a cycle problem. Perimenopause is a declining and erratic estrogen problem. Luteal-phase symptoms are usually progesterone-relative-to-estrogen. Estrogen dominance is often a clearance problem rather than a production one. Those need different arms, and the mistake that costs the most time is running a perimenopause approach on PCOS or vice versa. Cycle tracking is the measurement tool here, more than bloodwork — because hormones change daily and a single draw without a cycle day attached is close to meaningless.
On the bloodwork
Timing is everything on this panel and most are drawn wrong. Day 3 of your cycle for FSH, LH and estradiol — that is the baseline everything is compared against. Day 21, or seven days after ovulation, for progesterone — drawn at any other point it tells you nothing about whether you ovulated. The LH:FSH ratio is the classic PCOS signal and you only see it on a day-3 draw. AMH indicates ovarian reserve and is the fertility planning number. Prolactin and thyroid are the two that get skipped and both cause cycle irregularity — a prolactinoma is treatable and presents exactly like this. Thyroid antibodies matter because autoimmune thyroid disease is far more common in women and travels with cycle problems. Ferritin because heavy periods deplete iron, and that is the commonest cause of fatigue in this population by a distance.
The later draws
Around week 8, and after
Around week 8
The short list, drawn while you are running it. Not a progress report - it is the draw that catches the things that go wrong quietly.
The 3 markers in it
3 markers, about $82 at list. Drawn at Quest, no doctor’s visit.
After
Drawn at the end, against your own baseline. This is what turns the protocol into information rather than a feeling.
The 6 markers in it
LH & FSH, Estradiol, Standard (ECLIA), Progesterone, Total Testosterone, Fasting Insulin, Ferritin.
6 markers, about $146 at list. Drawn at Quest, no doctor’s visit.
Before any of it: the foundation
- Sleep — 7–9 h, consistent timing
Growth hormone is released in pulses during deep sleep, insulin sensitivity is measurably worse after one bad night, and appetite regulation collapses without it. Every compound below works through a system that sleep already governs. This is not filler advice — it is the highest-leverage item on the page and it is free.
- Protein — 1.6–2.2 g/kg bodyweight daily
The single dietary variable with the most consistent evidence behind it for body composition, in both directions — building and preserving. Under-eating protein while running anything anabolic is paying for a signal with no substrate to act on.
- Resistance training — 3–4 sessions weekly, progressive
Nothing here substitutes for mechanical tension. Compounds change how well you recover from and adapt to training; they do not replace the stimulus. A protocol run without training reliably produces the side effects and not the results.
- Steps — 8,000–12,000 daily
Non-exercise activity is the largest and most variable component of daily energy expenditure, and it is the one that quietly falls when you start dieting. Tracking it stops the metabolic adaptation people blame on their thyroid.
Who this is for, and who it is not
A woman with cycle symptoms, PCOS, perimenopausal change or fertility questions. This is the goal where the arms are least interchangeable — PCOS and perimenopause need almost opposite approaches, and the arm you need is decided by which one you are in.
Can you run all of them? Yes, and here is what it costs
These add up, and the clearance arm supports the others rather than competing with them. The cost: everything here is read across cycles, so stacking makes a three-month result harder to attribute. Track symptoms by cycle day either way.
How to read the picks
How to read this
Five arms, and you need the one matching your situation — not several. Vitex and black cohosh in particular are for different life stages and running both is incoherent. Identify which of the five descriptions is yours before buying anything.
On the evidence
Said once. This goal has better evidence than most on the site — myo-inositol in PCOS, vitex for luteal symptoms and black cohosh for vasomotor symptoms all have real randomized data. Unproven is not the same as ineffective, and each item's page carries its full tier. One caution specific to this page: anything hormonally active interacts with hormonal contraception and with pregnancy. Where that matters it is stated on the item.
Each pick names what it was chosen over and why. If you disagree with a choice, the alternative is right there and swapping it does not break the rest.
Phase one: what starts first
Weeks 1–4, 3 items, free in full
One arm, chosen by which description fits.
Starts in weeks 1–4: Myo-Inositol, Vitex (Chasteberry), DIM.
These two are alternatives, not a stack — inositol if PCOS, vitex if luteal symptoms. Start cycle tracking now: cycle length, symptom timing, basal temperature if you are willing. It is the measurement that makes the rest interpretable.
A general protocol, on purpose
It is built for the common case, not for you specifically. Compound selection and dosing genuinely do change person to person: training age, bloodwork, what you have run before, what you react to. Adjust it against your own numbers using the panels above, or if you want it built around your labs rather than the average, that is what 1-on-1 coaching is for. Between the two: fifteen minutes with Cam is $75.
The 16-week schedule
5 phases; the order is the members’ half
- Weeks
- 16
- Phases
- 5
- Items
- 5
- Arms
- 5
Identify and start the matching arm
One arm, chosen by which description fits.
These two are alternatives, not a stack — inositol if PCOS, vitex if luteal symptoms. Start cycle tracking now: cycle length, symptom timing, basal temperature if you are willing. It is the measurement that makes the rest interpretable.
Three full cycles before judging
This goal moves slowly and there is no shortcut.
Hold and track
Nothing new goes in. Clearance support started early because metabolite ratios are read across a full cycle, not a fortnight.
Re-assess against your tracking
Cycle data plus a repeat panel, timed properly.
Track the cycle, not the calendar
Three months of symptom tracking beats any single draw.
Adjusting it
5 situations come up on nearly every run
A protocol you cannot adjust is a protocol you abandon. 5 situations come up on nearly every run of this — no change after 3 cycles on vitex, cycle got more irregular after starting, PCOS symptoms improving but cycles still irregular and heavy periods getting worse, and 1 more. Each one has a specific answer, and the decision rules are inside Skool.
The lines I’d stop at
- Bleeding between periods, after sex, or after menopause. That needs assessment regardless of how minor it seems.
- Severe pelvic pain, or pain that is getting worse cycle on cycle. Endometriosis takes an average of seven years to diagnose partly because it gets normalized as bad periods.
- A positive pregnancy test — stop everything hormonally active immediately and continue only folate. Vitex, black cohosh and DIM have no pregnancy safety data worth relying on.
- Any bleeding after menopause, bleeding between periods, or bleeding after sex. That always needs assessment and it is never something to supplement around.
- Severe one-sided pelvic pain, particularly with a missed period. Ectopic pregnancy is an emergency.
- A new breast lump, skin dimpling or nipple change — and stop anything hormonally active until it has been assessed.
The schedule for this blueprint is inside Skool
Everything above is free and stays free. What you cannot get anywhere else is the order, and the order decides whether 16 weeks of effort compounds or just runs in parallel.
- The remaining 4 phases in full, with what each one changes
- The dose for every item in every phase, and why they differ by phase
- The 5 decision rules for when it is not working
5.0 (15 reviews)1,500+ members

Want it built around you?
1-on-1 coaching
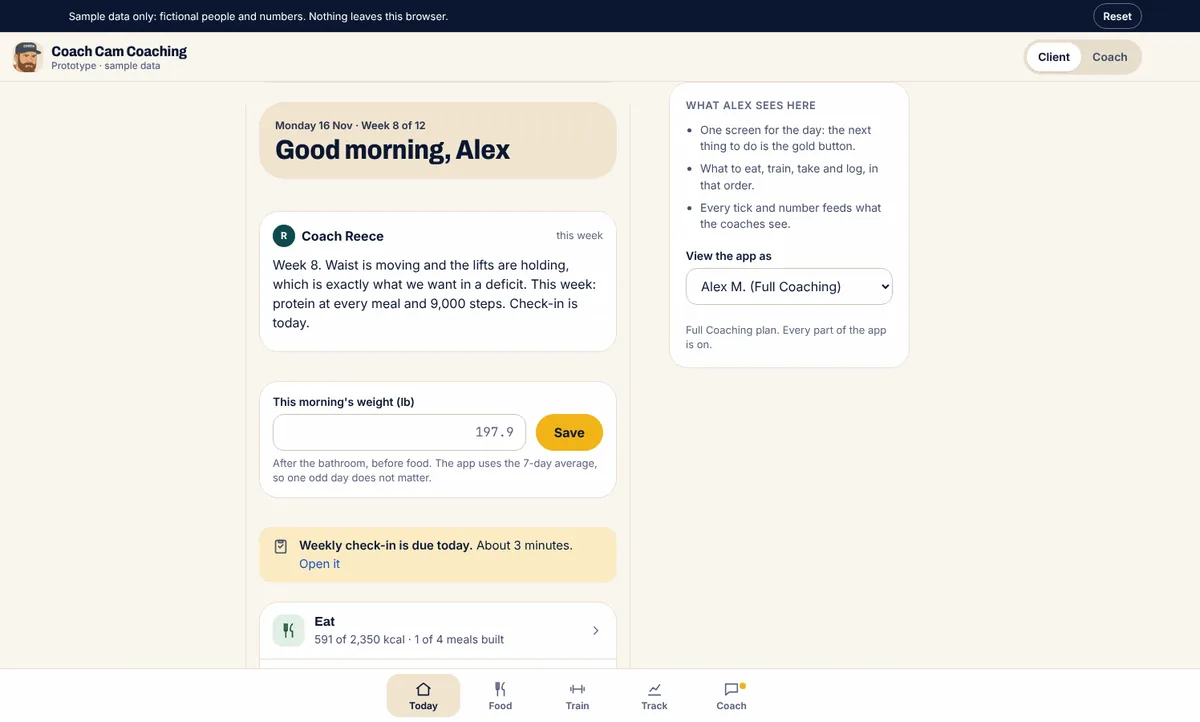
Cam and Coach Reece build training, nutrition, protocol and bloodwork around you. It starts with a free call.
from $150/mo
Apply for coaching
Ask Cam one question
Fifteen minutes on one topic, usually enough to settle which option is yours.
$75 per call
Book 15 minutesEducational and research reference only. Not medical advice, and not a prescription. Statements have not been evaluated by the FDA. This page contains affiliate links; Cam may earn a commission at no extra cost to you. Disclaimer